Low Anti-Müllerian Hormone: What It Means and Whether You Can Have a Baby

Seeing a low number next to the letters AMH on your results can raise many questions, and the most immediate one is usually whether you can still have your baby. It is a valid concern. Anti-Müllerian hormone is a useful marker, although it says less than people often think.
In this post we explain what it really measures, how it is interpreted and which paths may exist from that result.
Low anti-Müllerian hormone: what it measures and what your result tells you
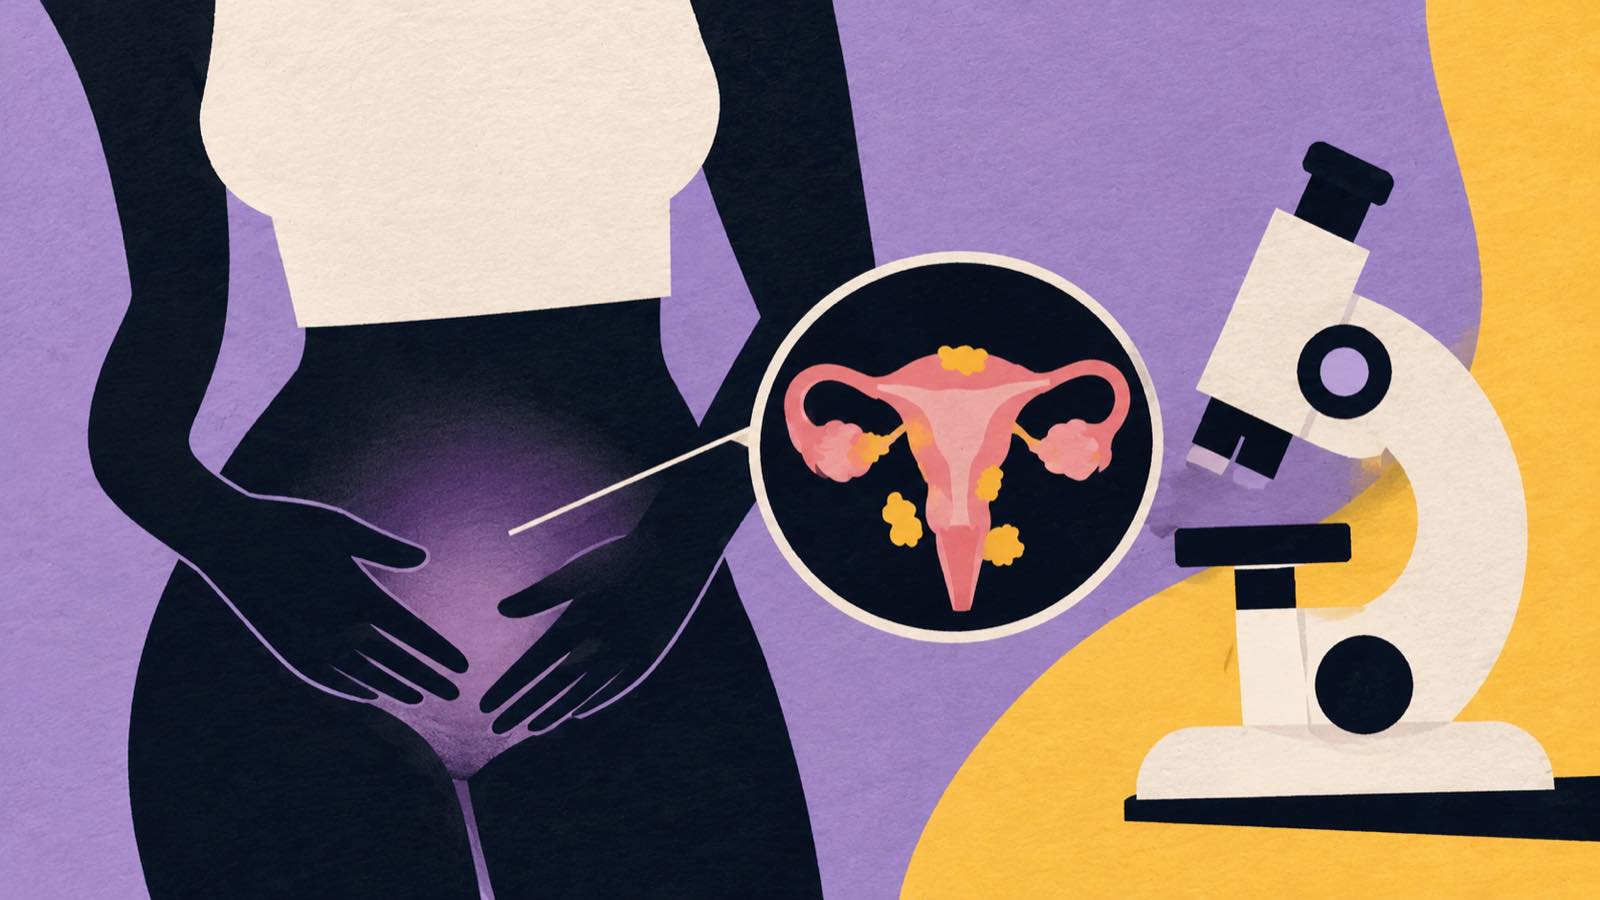
Anti-Müllerian hormone, known as AMH, is produced by the cells surrounding the small follicles that are growing inside the ovaries. The more follicles of this kind there are, the higher the AMH in the blood tends to be. That is why it is used as a way to estimate ovarian reserve, meaning the number of eggs still available.
A practical advantage of this test is that it can be taken on almost any day of the cycle, and its value changes little from one month to the next. That makes it a convenient and fairly stable marker for getting a reference of your reserve.
That said, AMH measures quantity. Egg quality, which has a big influence on whether an embryo develops, depends mostly on age and is not reflected in this number. Besides, to achieve a pregnancy it is enough for at least one egg to give rise to an embryo, even if the reserve is small.
Some studies in women trying to conceive naturally found that a low AMH did not, on its own, reduce the likelihood of getting pregnant in the following months when compared with women of the same age with normal values. This suggests that a low AMH is not the same as infertility, although it does provide relevant information for planning.
Having low anti-Müllerian hormone does not mean, on its own, that you can’t have a baby. It usually indicates that your reserve is lower than expected, and that information can help you make decisions about the timing and the options that suit you best.
Your age and other factors that change how AMH is read
The same AMH number can mean very different things depending on the age of the person receiving it. Reference values change over the years and also between laboratories, which is why your result is always compared with what is expected for your age.
At 30, a low AMH may indicate that the reserve is declining earlier than usual, although the eggs available usually keep good quality. At 40, the same value may be closer to what is expected, but at that stage egg quality tends to be the factor with the most influence. In each case, the conversation with your specialist shifts its focus.
There are also situations that can lower AMH without meaning the same thing for every woman:
- Hormonal contraceptives can temporarily lower the value, which usually recovers a few months after stopping them.
- Ovarian surgery, for example to remove endometriosis cysts, can reduce part of the ovarian tissue.
- Cancer treatments, such as chemotherapy, can affect the reserve, a topic we cover in our post on fertility after cancer.
- Smoking has been associated with an earlier decline in reserve, one of the habits that also influence egg quality according to epigenetics and fertility.
- Some genetic or autoimmune conditions can bring forward the decline in reserve.
At the other extreme, a very low AMH at a young age may lead your specialist to rule out premature ovarian insufficiency, a condition in which the ovaries stop working regularly before the age of 40.
For all these reasons, age carries a lot of weight in the interpretation, but it doesn’t settle it alone. Your history, your menstrual cycles and the results of other tests complete the meaning of the number.

Hormonal contraceptives can temporarily lower AMH; the value usually recovers months after stopping them
How AMH is interpreted alongside other markers
To understand your ovarian reserve more precisely, your specialist usually cross-checks AMH with other data. Each marker looks at the reserve from a different angle, and together they form a more reliable picture.
The AMH value and its units. Results can be expressed in nanograms per milliliter (ng/mL) or in picomoles per liter (pmol/L), so it is worth checking the unit before comparing with any chart. As a general guide, many specialists consider an AMH below around 1 ng/mL to be low, although the cutoff varies by age and laboratory. That is why two results from different laboratories may not be directly comparable.
FSH and estradiol at the start of the cycle. Follicle-stimulating hormone (FSH) is measured between the second and fourth day of menstruation, together with estradiol. When the reserve declines, the body tends to produce more FSH to stimulate the ovaries. This marker can vary from one cycle to the next, so it is interpreted with caution and almost always alongside AMH.
Antral follicle count. Through a transvaginal ultrasound performed in the first days of the cycle, the small follicles visible in both ovaries are counted. This figure is closely related to AMH, and when the two agree, the conclusion is more solid. When they don’t, your specialist may repeat a test or consider other factors.
Read together, these markers mainly help anticipate how your ovaries might respond to a stimulation treatment. The question of whether you will be able to have your baby is better answered by adding your age, your history and, when relevant, your partner’s evaluation.
Low AMH and options for having a baby: when to seek guidance
With a low AMH, time becomes a resource worth protecting. Seeking guidance early lets you learn about your options while more of them are still available, and choose with information in hand.
It is worth seeking an evaluation, without waiting for the general timelines we describe in our post on when to see a fertility specialist, if:
- Your AMH result came back low and you are already trying for a pregnancy.
- You don’t want to try for a baby yet, but you would like to in a few years.
- Your AMH came back very low and you are under 35.
- Your cycles have become shorter or irregular in recent months.
- You have a history of ovarian surgery or cancer treatment.
The options depend on your age, your markers and your plans. If you are not trying for a pregnancy yet, egg freezing can help you preserve eggs of your current age to use later. If you are already trying, in some cases it may be worth continuing naturally for a defined period, and in others it is better to move on to IVF with a stimulation protocol adjusted to your reserve. In some cases your specialist may consider regenerative medicine programs such as Ovagen®, aimed at ovarian reserve, or egg donation when the other alternatives are less likely to work.
At Ingenes, your AMH result is the start of the conversation. Our reproductive medicine specialists interpret your markers together, consider your history and your life plans, and clearly explain the advantages and limits of each option so that the decision is yours.
If you want to resolve your doubts with someone who reviews your tests with you, your first consultation is a good place to start. You can schedule it whenever you feel ready.
Frequently asked questions
What is anti-Müllerian hormone and what does it measure?
AMH is produced by the small growing follicles inside the ovaries. Its level in the blood is used to estimate ovarian reserve, meaning how many eggs are still available. It does not measure egg quality.
What AMH value is considered low?
As a general guide, many specialists consider an AMH below around 1 ng/mL to be low, but the cutoff depends on age and the laboratory. Check the unit (ng/mL or pmol/L) before comparing with any chart.
Can I get pregnant naturally with low AMH?
Yes, it is possible. Studies in women trying to conceive naturally found that a low AMH, on its own, did not reduce the likelihood of getting pregnant in the following months compared with women of the same age with normal values.
Does AMH change with the cycle or with contraceptives?
It changes little over the cycle, which is why it can be measured on almost any day. Hormonal contraceptives can lower it temporarily; the value usually recovers a few months after stopping them.
What are my options if my AMH is low?
They depend on your age and your plans: freezing eggs if you are not trying for a pregnancy yet, IVF with a protocol adjusted to your reserve, programs such as Ovagen® aimed at ovarian reserve or, when the other alternatives are less likely to work, egg donation.
A number that invites you to plan
A low AMH speaks to how many eggs are left, and leaves the most important question open: what you can do with the ones you have. That number invites you to plan more carefully, and many women with a lower reserve than expected have gone on to hold their baby in their arms.
Take the time to understand your result without comparing yourself to anyone. Your history, your age and your plans are what give meaning to any figure.
And if at some point you want to look at those numbers with someone by your side, at Ingenes you will find a team ready to go through them with you, step by step.
Sources
- Cleveland Clinic. Anti-Mullerian Hormone (AMH) Test: Purpose, Levels & Results. my.clevelandclinic.org
- Practice Committee of the American Society for Reproductive Medicine. Testing and interpreting measures of ovarian reserve: a committee opinion. Fertility and Sterility, 2020. pubmed.ncbi.nlm.nih.gov
- Steiner A. Z. et al. Association Between Biomarkers of Ovarian Reserve and Infertility Among Older Women of Reproductive Age. JAMA, 2017. pubmed.ncbi.nlm.nih.gov
- Ferraretti A. P. et al. ESHRE consensus on the definition of 'poor response' to ovarian stimulation for in vitro fertilization: the Bologna criteria. Human Reproduction, 2011. pubmed.ncbi.nlm.nih.gov